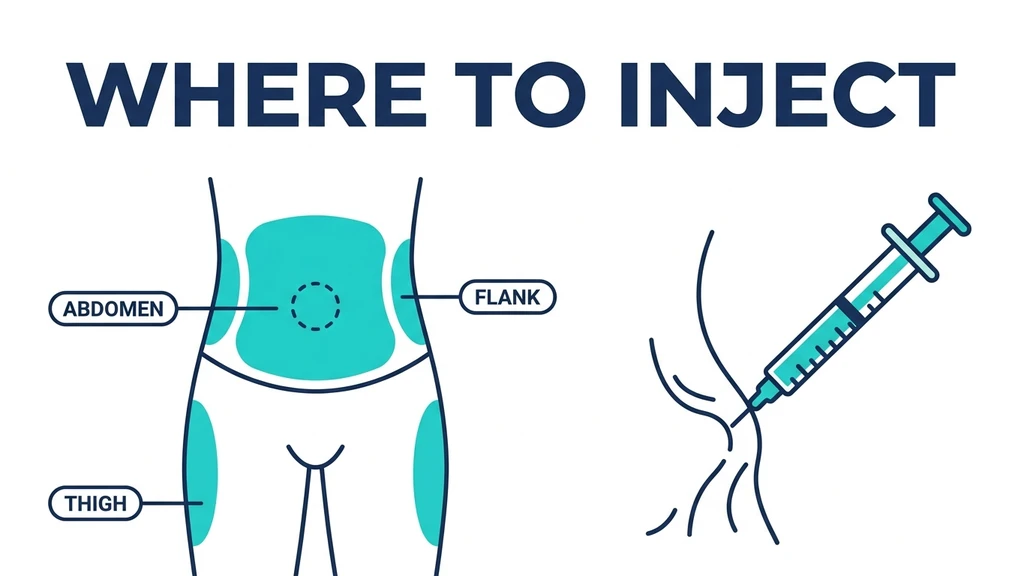
The vial is mixed, the syringe holds tonight's dose, and you are standing in the bathroom wondering where the needle goes. Here is the answer: inject CJC-1295 and ipamorelin into subcutaneous belly fat, at least 2 inches from your navel, with a 29 to 31 gauge insulin syringe. The front of the thigh, the love handles, and the back of the arm are your rotation alternatives. Both peptides go in one syringe, one site, one stick.
| Site | Landmark | Pinch needed? | Self-injection ease | Best for |
|---|---|---|---|---|
| Abdomen | 2+ inches from navel, above or beside it | Yes, light | Easiest | Daily default |
| Front-outer thigh | Middle third, outer half | Yes on lean legs | Easy | Alternating weeks |
| Love handles | Above the hip bone, toward the side | Yes | Moderate | Extra rotation room |
| Back of upper arm | Lower third, over triceps | Yes | Hard alone | When someone helps |
This page covers sites, rotation, and timing only. For how much to draw, use the CJC-1295 dosage guide and the CJC-1295/ipamorelin dosage calculator.
Get your custom peptide protocol:
- Tailored to your body and goals
- Precise dosing and cycle length
- Safe stacking combinations
- Backed by peer-reviewed studies
- Ready in under 2 minutes
Site-by-Site Walkthrough
Every site below reaches the same target: the fat layer between skin and muscle. CJC-1295 and ipamorelin are dosed subcutaneously, and the clinical work behind CJC-1295 used exactly that route (Teichman et al., J Clin Endocrinol Metab, 2006, PMID 16352683).
Standard equipment is a 29 to 31 gauge insulin syringe with a 5/16 inch (8 mm) needle. Pinch a fold of skin, insert at 45 degrees, and push the plunger slowly. If you carry enough fat at the site, 90 degrees without a deep pinch also lands subcutaneous. Aspiration is unnecessary for subcutaneous injections.
Abdomen
Stay at least 2 inches from the navel in every direction. The tissue ring around the navel is denser and more vascular, which means more bruises and less predictable absorption.
Avoid the waistband line. Fabric friction on a fresh injection site keeps it irritated for days. Pick a spot, note it, and place tomorrow's dose at least 1 inch away.
Thigh
Use the middle third of the front-outer thigh. Sit down, let the muscle relax, and pinch the fat fold before inserting.
Lean users often have thin thigh fat. If the pinch feels like skin over rock, use 45 degrees and a shallow fold, or move back to the abdomen.
Love Handles and Back of the Arm
The flank above the hip bone gives most people a generous fat fold and doubles your rotation real estate. Reach across your body or use a mirror the first time.
The back of the upper arm works best with a second person pinching the fold. Alone, you can press the arm fat against a wall or door frame to bunch it, but the abdomen stays the easier choice. Full technique basics live in the peptide injection guide.
Does the Site Change Absorption?
Subcutaneous injection is the studied route for these peptides. CJC-1295 given subcutaneously raised GH 2 to 10 fold and IGF-1 1.5 to 3 fold in healthy adults, with effects lasting days (Teichman et al., J Clin Endocrinol Metab, 2006, PMID 16352683). That is the evidence base. Site-to-site absorption differences between belly and thigh are documented for insulin, and no equivalent head-to-head data exists for CJC-1295 or ipamorelin.
So pick sites by comfort and rotation, and ignore absorption folklore. Intramuscular injection has no demonstrated benefit for these peptides. It reaches deeper, hurts more, bleeds more, and leaves the studied route behind.
One syringe covers both compounds. Drawing CJC-1295 and ipamorelin together is standard practice; the reconstitution walkthrough for CJC-1295 and ipamorelin shows the two-vial draw, and the general reconstitution guide covers mixing technique.
A Rotation Map That Actually Prevents Lumps
Repeated injections into the same spot build lipohypertrophy: a rubbery fat lump under the skin that absorbs drugs erratically. The numbers come from people who inject daily, just like a GH peptide protocol. In 430 insulin-injecting patients, 64.4% had lipohypertrophy. Among those with lumps, 98% rotated incorrectly or not at all. Among correct rotators, only 5% had them (Blanco et al., Diabetes Metab, 2013, PMID 23886784).
That is the whole case for rotation, measured in the same subcutaneous tissue you are using. The fix costs nothing: a six-station loop.
| Night | Site |
|---|---|
| 1 | Left abdomen |
| 2 | Right abdomen |
| 3 | Left thigh |
| 4 | Right thigh |
| 5 | Left love handle |
| 6 | Right love handle |
| 7 | Back to left abdomen, 1 inch from night 1 |
Keep every stick at least 1 inch from the last one at that station. If you find a firm, rubbery patch, retire that zone for several weeks and let it recover. Injecting into a lump wastes the dose you paid for: absorption from hypertrophied tissue is unpredictable.
When to Inject: Meals and Sleep
Inject 30 to 60 minutes before bed, on an empty stomach: roughly 2 hours after your last meal, and wait at least 20 to 30 minutes before eating anything after. Bedtime dosing stacks the peptides on top of the natural GH pulse that arrives with deep sleep.
The empty stomach rule has a mechanism behind it. Glucose ingestion triggers somatostatin release from the hypothalamus, and somatostatin is the brake on GH secretion (Shibasaki et al., Life Sci, 1989, PMID 2563893). Inject right after dinner and you are asking the pituitary to fire while the brake is pressed.
Ipamorelin suits bedtime use because of its selectivity. It releases GH without pushing ACTH or cortisol beyond GHRH-like levels (Raun et al., Eur J Endocrinol, 1998, PMID 9849822), so it does not wire you awake the way older secretagogues could. Timing decides when the pulse fires; dose size decides how big it is, and that lives in the CJC-1295 dosage guide.
Injection Site Reactions: Normal vs Not
A small red welt that itches for 10 to 60 minutes is the most common reaction, especially with ipamorelin. Users describe it as a histamine-like flare. It fades on its own and does not predict anything systemic. Mild bruising happens when the needle nicks a capillary; it is cosmetic.
Spreading redness, warmth, swelling that grows after day one, pus, or fever is a different category. That pattern suggests infection and deserves medical attention, not another injection.
To shrink the welts: hold the refrigerated syringe in your hand for 1 to 2 minutes so the solution warms, let the alcohol dry completely before inserting, inject over 5 to 10 seconds, wait 5 seconds before withdrawing, and skip rubbing the site. A fresh needle every time is non-negotiable; reused needles dull, drag, and contaminate. Storage and shelf-life rules for the mixed vial are in the reconstituted peptide shelf-life guide, and systemic effects are covered in the CJC-1295 and ipamorelin side effects guide.
Mistakes That Actually Cost You
Hitting muscle on a lean frame. No pinch, a 90 degree angle, and low body fat sends the needle through the fat layer into muscle: sharper pain, more bruising, and an unstudied absorption profile. Fix: 5/16 inch needle, a real pinch, 45 degrees.
Same-spot loyalty. The Blanco data splits 98% versus 5% on rotation alone (Blanco et al., Diabetes Metab, 2013, PMID 23886784). One favorite spot becomes one lump, and every future dose placed there underperforms. Fix: the six-station loop above.
Injecting after dinner. The glucose-driven somatostatin brake blunts the GH response. You feel nothing fail; the protocol just quietly underdelivers. Fix: 2 hours after the last meal, every time.
Injecting through the navel zone or waistband line. Denser tissue, more vessels, constant fabric friction. Fix: 2 inches of clearance from the navel and a site your waistband never touches. The same landmarking logic applies to other GH peptides, covered in the sermorelin injection site guide.
Frequently Asked Questions
Can I inject CJC-1295 and ipamorelin in the same syringe?
Yes. Drawing both peptides into one insulin syringe and injecting them at one subcutaneous site is standard practice. The two-vial draw order and the math are covered in the CJC-1295 and ipamorelin reconstitution guide.
Is the stomach better than the thigh for absorption?
No absorption difference has been demonstrated between subcutaneous sites for these peptides. The abdomen wins on convenience: easier pinch, easier reach, more rotation room. Pick by comfort and follow the rotation map in the peptide injection guide.
Why do I get a red welt after injecting ipamorelin?
A histamine-like local flare lasting 10 to 60 minutes is the most reported reaction to ipamorelin. It is normal if it fades within an hour. Warm the solution in your hand, inject slowly over 5 to 10 seconds, and rotate sites to reduce it.
Do I need to inject on an empty stomach?
Yes. Glucose triggers somatostatin, the hormone that suppresses GH release (Shibasaki 1989, PMID 2563893). Inject roughly 2 hours after your last meal and wait 20 to 30 minutes before eating. Dose sizing lives in the CJC-1295 dosage guide.
Can I inject CJC-1295 and ipamorelin into muscle?
Subcutaneous fat is the route used in the CJC-1295 clinical trials (Teichman 2006, PMID 16352683). Intramuscular injection adds pain, bruising, and an unstudied absorption profile with no established benefit. Stay subcutaneous, per the complete injection guide.
How far from my belly button should I inject?
Keep at least 2 inches of clearance in every direction. The peri-navel ring is denser and more vascular, which means more bruising and less consistent uptake. Details on abdominal landmarking are in the peptide injection guide.
How often should I rotate injection sites?
Every single injection. Never hit the same spot twice in a row, and keep consecutive sticks at least 1 inch apart. In insulin users, 98% of lipohypertrophy cases traced to poor rotation versus 5% in correct rotators, a pattern covered with the CJC-1295 and ipamorelin side effects.
What needle size for CJC-1295 and ipamorelin?
A 29 to 31 gauge insulin syringe with a 5/16 inch (8 mm) needle. Insert at 45 degrees with a pinched skin fold, or 90 degrees if the site carries ample fat. Verify your draw volume with the CJC-1295/ipamorelin dosage calculator.
The Bottom Line
Belly fat, 2 inches off the navel, 29 to 31 gauge needle, rotate six stations, inject 30 to 60 minutes before bed on an empty stomach. That single sentence is 90% of injection-site technique for CJC-1295 and ipamorelin.
The principle underneath: these peptides work by timing a pulse, so the site matters less than the rotation and the clock. Protect the tissue, protect the timing.
Dial in your exact draw with the CJC-1295/ipamorelin dosage calculator, and read the CJC-1295 ipamorelin benefits guide for what the protocol delivers. CJC-1295 and ipamorelin are research compounds, not FDA-approved therapies; this content is educational, not medical advice.
Related Articles
How to Reconstitute CJC-1295 and Ipamorelin (Unit Math)
Reconstitute CJC-1295 and ipamorelin: 2 mL bacteriostatic water per 5 mg vial = 25 mcg per unit. Water volumes, unit tables, blend rules, storage.
Peptides for Bodybuilding (2026)
Best peptides for bodybuilding: BPC-157, TB-500, MK-677, CJC-1295/Ipamorelin, HGH Fragment 176-191. Dosages and stacking protocols.
CJC Peptide: Which CJC-1295 Are You Holding?
CJC peptide explained: CJC-1295 with DAC (6-8 day half-life) versus CJC-1295 no DAC, which is Mod GRF 1-29. How to identify the vial you actually hold.
Where to Inject MOTS-c: Best Sites & Technique
Where to inject MOTS-c: best subcutaneous sites (abdomen, thigh, love handles), needle gauge, step-by-step technique, and rotation to avoid bruising.