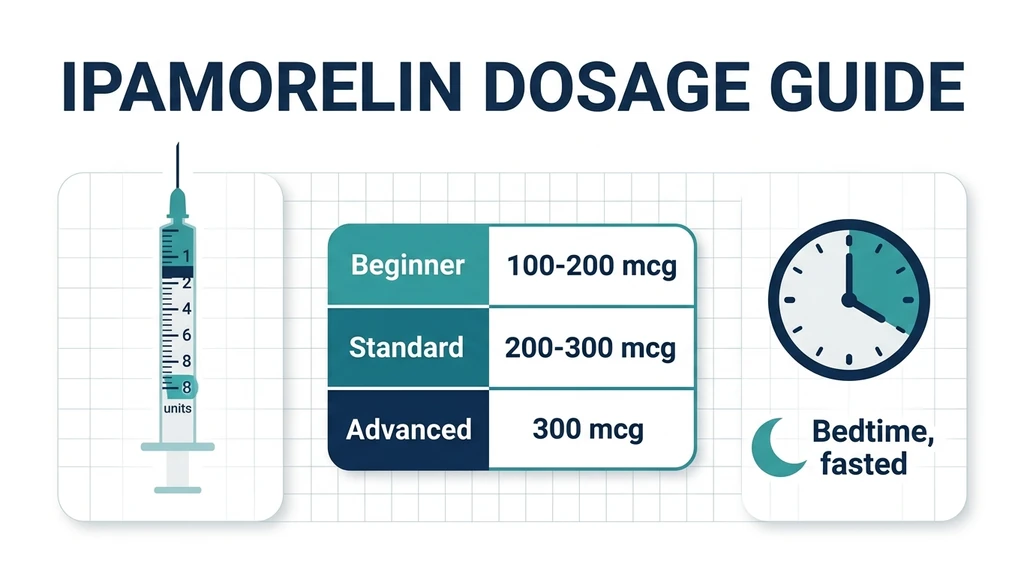
You have a 5 mg vial of ipamorelin and three Reddit protocols that contradict each other. Here is the answer: the standard solo ipamorelin dose is 200 to 300 mcg, injected subcutaneously 1 to 3 times per day, with the bedtime injection on an empty stomach as the one that matters most. Cycles run 8 to 12 weeks, followed by 4 weeks off.
| Parameter | Standard protocol |
|---|---|
| Dose per injection | 200-300 mcg |
| Frequency | 1-3x daily, 3+ hours apart |
| Priority injection | Bedtime, 2+ hours after last meal |
| Route | Subcutaneous, insulin syringe |
| Half-life | ~2 hours |
| GH peak | ~40 minutes post-injection |
| Cycle | 8-12 weeks on, 4 weeks off |
This guide covers solo ipamorelin only. If you are running the blend with CJC-1295, the numbers change; those protocols live in the CJC-1295 dosage guide.
Get your custom peptide protocol:
- Tailored to your body and goals
- Precise dosing and cycle length
- Safe stacking combinations
- Backed by peer-reviewed studies
- Ready in under 2 minutes
How Ipamorelin Works, and Why Timing Beats Size
Ipamorelin is a ghrelin receptor agonist. It binds GHS-R1a in the pituitary and triggers a pulse of your own stored growth hormone.
Think of it as a doorbell, not a delivery truck. Pressing the doorbell tells the pituitary to release what it already stocked; pressing harder does not make the warehouse bigger. Literally stated: ipamorelin stimulates release of endogenous GH in a pulse, and past a certain dose the pulse stops growing.
The human pharmacokinetics back the timing rules. In 40 healthy volunteers, GH peaked about 40 minutes after dosing and fell back within roughly 6 hours, with a terminal half-life near 2 hours (Gobburu et al., Pharm Res, 1999, PMID 10496658). A short pulse that you can place deliberately is the entire point: put it on top of the natural slow-wave-sleep GH surge and the two stack.
Selectivity is what separates ipamorelin from the older secretagogues. At GH-releasing doses it does not push ACTH or cortisol beyond what GHRH itself produces, and it leaves prolactin essentially alone, unlike GHRP-2 and GHRP-6 (Raun et al., Eur J Endocrinol, 1998, PMID 9849822). Downstream, the GH pulse does what GH does: in rats, ipamorelin produced measurable longitudinal bone growth (Johansen et al., Growth Horm IGF Res, 1999, PMID 10373343).
Ipamorelin Dosage Chart by Goal and Body Weight
Goal determines frequency more than dose size. The per-injection amount stays inside 100 to 300 mcg for almost everyone.
| Goal | Dose per injection | Injections per day | Timing |
|---|---|---|---|
| Sleep, recovery, first cycle | 100-200 mcg | 1 | Bedtime |
| Standard recomposition | 200-300 mcg | 2 | Morning fasted + bedtime |
| Aggressive protocol | 300 mcg | 3 | Morning, mid-afternoon, bedtime |
The community weight heuristic runs about 1 mcg per kg per pulse: 60 kg lands near 60 to 180 mcg, 80 kg near 80 to 240 mcg, 100 kg near 100 to 300 mcg. Be clear about what that number is: a GHRP-class tradition, not the product of an ipamorelin dose-finding trial. No such trial exists.
No validated women-specific dose exists either. Community practice runs 100 to 200 mcg per injection, and the saturation logic below applies identically. For a side-by-side of how ipamorelin dosing compares with the GHRH analogs, see tesamorelin vs sermorelin vs ipamorelin; the full multi-peptide reference lives in the peptide dosage chart.
The Saturation Dose: Why 500 mcg Is Not Better Than 300
The Gobburu PK/PD model found dose-proportional plasma levels but a saturable GH response: output approaches a ceiling as concentration rises, with a half-maximal stimulatory concentration of 214 nmol/L (Gobburu et al., Pharm Res, 1999, PMID 10496658). Past the ceiling, extra micrograms buy side-effect exposure, not growth hormone.
The practical rule: cap single injections around 300 mcg. If you want more total stimulation, add a second daily pulse instead of inflating the first one. Two 200 mcg pulses spaced 8 hours apart beat one 400 mcg pulse, because each catches the pituitary restocked.
This is also the argument against dose creep mid-cycle. Feeling less from week 6 is not fixed by 450 mcg; it is a signal to check timing, food spacing, and product quality first.
Timing Protocols: 1x, 2x, 3x Daily and the 5/2 Schedule
Once daily (bedtime). The entry protocol and the one with the best effort-to-return ratio. Inject 30 to 60 minutes before sleep, at least 2 hours after your last meal, and wait 30 minutes before any food. The injection rides the natural nocturnal GH pulse.
Twice daily. Add a morning injection, fasted, at least 30 minutes before breakfast. Keep pulses 3 or more hours apart so the pituitary restocks between doorbell rings.
Three times daily. Morning, mid-afternoon (2 hours after lunch), bedtime. Reserved for aggressive recomposition phases; the third injection adds the least and costs the most discipline.
The 5/2 schedule. Five weekdays on, weekends off. It is a community hedge against receptor desensitization with no trial evidence behind it, and it cuts the weekly dose by about 28%. If you run it, run it knowingly.
Cycles run 8 to 12 weeks on, 4 weeks off. Ipamorelin-specific desensitization data is thin; the off-cycle convention is imported from secretagogue class practice. Where the needle goes, and the site rotation that protects your tissue, is covered in the CJC-1295 and ipamorelin injection site guide.
Reconstitution Math: 2 mg, 5 mg, and 10 mg Vials
Your dose in micrograms means nothing until you know the concentration you created. One worked example: add 2.5 mL of bacteriostatic water to a 5 mg vial and you get 2,000 mcg/mL, which is 20 mcg per unit on a U-100 insulin syringe. A 200 mcg dose is 10 units.
| Vial | Bac water | Concentration | 100 mcg | 200 mcg | 300 mcg |
|---|---|---|---|---|---|
| 2 mg | 1 mL | 2,000 mcg/mL | 5 units | 10 units | 15 units |
| 5 mg | 2 mL | 2,500 mcg/mL | 4 units | 8 units | 12 units |
| 5 mg | 2.5 mL | 2,000 mcg/mL | 5 units | 10 units | 15 units |
| 10 mg | 3 mL | 3,333 mcg/mL | 3 units | 6 units | 9 units |
Use bacteriostatic water, never plain sterile water, for a vial you will puncture nightly for weeks; the bacteriostatic vs sterile water guide explains the preservative math. Full technique, including the two-vial single-syringe draw for stack users, is in the CJC-1295 and ipamorelin reconstitution guide.
After mixing, refrigerate at 2 to 8 degrees C and plan to finish the vial within 4 to 6 weeks; the reconstituted shelf-life guide covers the decay timeline. Check any vial-plus-water combination with the peptide reconstitution calculator.
Side Effects and the Safety Ceiling: What the Numbers Say
Community-reported side effects at standard doses are mild and transient: brief headache, flushing, water retention, injection-site redness, and a wave of hunger 20 to 40 minutes post-injection. The hunger is mechanistic, a ghrelin-mimetic effect documented in animal models (Venkova et al., J Pharmacol Exp Ther, 2009, PMID 19289567). Tingling hands or carpal-tunnel-like pressure signals GH excess: drop the dose.
The best safety-ceiling data comes from a hospital trial. In a randomized study of 114 bowel-resection patients, IV ipamorelin at 0.03 mg/kg twice daily for up to 7 days produced an adverse-event profile comparable to placebo (Beck et al., Int J Colorectal Dis, 2014, PMID 25331030). For an 80 kg adult that is roughly 2,400 mcg per dose, about 10 times community subcutaneous levels, tolerated at placebo level for a week.
The honesty beat belongs next to that number: the same trial failed its efficacy endpoint, and no human trial has ever tested ipamorelin for muscle gain, fat loss, or anti-aging. The class review is equally blunt: efficacy and safety data in healthy adults are limited, long-term safety is unestablished, and anyone running a secretagogue should watch IGF-1 and fasting glucose (Sigalos et al., Sex Med Rev, 2018, PMID 28400207).
Skip ipamorelin entirely with active or prior cancer, uncontrolled blood sugar, pregnancy or breastfeeding, or open growth plates. Stack-specific reactions are covered in the CJC-1295 and ipamorelin side effects guide.
Common Ipamorelin Dosing Mistakes
Chasing bigger single doses. The GH response saturates. 500 mcg delivers the side effects of 500 mcg and the GH of 300 mcg. Fix: cap the pulse, add a second one.
Injecting fed. Insulin and glucose blunt the GH pulse. A bedtime dose 30 minutes after dessert quietly underdelivers all cycle. Fix: 2 hours of fasting before, 30 minutes after.
Misreading the syringe math. At 10 mg reconstituted in 1 mL, 2 units is a normal 200 mcg, but drawing 0.3 mL delivers 3,000 mcg, a 10x error from one misread barrel. Fix: compute mcg per unit once, write it on the vial, and verify with the unit converter.
Running blend numbers on a solo protocol. Stack dosing from CJC-1295 combos assumes two compounds splitting the work. Fix: solo protocols use this page; if you want the oral secretagogue route instead, weigh it against MK-677.
Skipping the off-cycle. 12 weeks on, zero off, repeated indefinitely is unstudied territory on a compound with no long-term human data. Fix: 4 weeks off after every cycle, bloodwork if you run multiple cycles per year. Related GHRP dosing patterns are in the hexarelin dosage guide.
Solo Ipamorelin vs the CJC-1295 Stack
Solo is the right call for a first secretagogue cycle, for sleep-and-recovery goals, and for anyone who wants the cleanest side-effect profile in the class. One compound, one variable, easy to read your own response.
The stack earns its complexity when the goal is body composition and you have a solo cycle behind you. CJC-1295 raises the baseline GHRH tone while ipamorelin fires the pulse, two different receptors pulling the same lever. Those protocols, ratios, and the DAC question live in the CJC-1295 dosage guide, with draw volumes handled by the CJC-1295/ipamorelin dosage calculator.
Frequently Asked Questions
How many mcg of ipamorelin should I take per day?
200 to 300 mcg per injection, 1 to 3 times daily, for a total of 200 to 900 mcg per day. Beginners start at one 100 to 200 mcg bedtime dose. The full protocol table is in the peptide dosage chart.
When is the best time to take ipamorelin?
Bedtime, 30 to 60 minutes before sleep, at least 2 hours after your last meal. GH peaks about 40 minutes post-injection and stacks on the natural sleep pulse. Injection site and rotation are covered in the injection site guide.
How many units is 200 mcg of ipamorelin on an insulin syringe?
At 5 mg reconstituted with 2.5 mL, 200 mcg is 10 units; with 2 mL, it is 8 units. Units equal dose divided by mcg-per-unit, which your water volume sets. Run your setup through the peptide reconstitution calculator.
How long should an ipamorelin cycle last?
8 to 12 weeks on, then 4 weeks off. The convention comes from secretagogue class practice rather than ipamorelin trials, so treat it as a floor, not a technicality. Comparisons across the class are in tesamorelin vs sermorelin vs ipamorelin.
Can I take ipamorelin once a day and still get results?
Yes. Bedtime-only at 100 to 200 mcg is the standard entry protocol and captures the highest-leverage pulse of the day. Add a fasted morning injection later if goals demand it, per the ipamorelin profile protocol cards.
Does ipamorelin raise cortisol or prolactin?
Not meaningfully at GH-releasing doses. Raun 1998 (PMID 9849822) found ACTH and cortisol responses no different from GHRH stimulation, the selectivity that separates it from GHRP-2 and GHRP-6.
What happens if I take too much ipamorelin?
The GH response saturates, so extra micrograms add water retention, tingling, and hunger without added benefit. In a hospital RCT, doses near 10x community levels were tolerated at placebo level for a week (Beck 2014, PMID 25331030). Side effects are detailed in the side effects guide.
Is ipamorelin safe long-term?
Unknown. No long-term human trials exist, and the class review (Sigalos 2018, PMID 28400207) recommends monitoring IGF-1 and fasting glucose on any secretagogue. Run defined cycles with off-weeks, and compare alternatives in MK-677 vs ipamorelin.
The Bottom Line
200 to 300 mcg subcutaneous, 1 to 3 times daily, bedtime fasted, 8 to 12 weeks on and 4 off. That is the whole solo protocol.
The principle underneath: ipamorelin is a pulse you place, not a level you maintain. Timing and food spacing move results more than any extra 100 mcg ever will.
Compute your exact draw with the peptide reconstitution calculator, and if you are weighing the stack, start with the CJC-1295 dosage guide. Ipamorelin is a research compound, not an FDA-approved therapy; this content is educational, not medical advice.
Helpful Tools
Related Articles
Sermorelin Dosage Chart by Goal & Weight
Sermorelin dosage chart: 200-500 mcg nightly before bed. Doses by goal and body weight, unit conversions for every vial size, timing, and titration.
CJC-1295 Dosage: Complete Protocol Guide
CJC-1295 dosage guide: DAC and no-DAC protocols. Dosing by goal (anti-aging, fat loss, muscle, sleep), ipamorelin stacking, and injection timing.
Tesamorelin Dosage Chart: Clinical Doses
Full tesamorelin dosage chart: the 2 mg/day clinical dose, research tiers, reconstitution math in syringe units, timing, titration, and cycle length.
DSIP Peptide Dosage: Sleep Protocols
DSIP dosage guide: 100-300 mcg protocols, reconstitution steps, timing before bed, cycling schedule, cortisol modulation, and delta-wave research.